BACKGROUND: Neuropathic pain is a common and difficult-to-treat complication of spinal cord injury (SCI). Virtual reality (VR)-based interventions have emerged as a non-pharmacological approach to pain modulation, but their efficacy remains uncertain. This meta-analysis evaluated the effect of VR-based interventions on neuropathic pain intensity in individuals with SCI.
METHODS: PubMed, Cochrane Library, Embase, Web of Science, Wanfang, and CNKI were searched through June 19, 2026. Randomized controlled trials (RCTs) comparing VR-based interventions with control conditions in adults with SCI-related neuropathic pain were included. Standardized mean differences (SMDs) with 95% confidence intervals (CIs) were pooled using a random-effects model accounting for the influence of potential heterogeneity.
RESULTS: Ten RCTs involving 317 participants contributed 12 comparisons. VR-based interventions significantly reduced neuropathic pain intensity compared with controls (SMD = -0.50, 95% CI -0.76 to -0.25; p < 0.001; I2 = 27%). Leave-one-out sensitivity analyses confirmed the robustness of the finding (SMD range, -0.42 to -0.60; all p < 0.05). No significant subgroup differences were observed according to study design, mean age, time since SCI, VR intervention type, intervention session pattern, comparator type, pain assessment scale, or risk-of-bias judgment (all p for subgroup differences > 0.05). Meta-regression analyses identified no significant effect modifiers. The certainty of evidence was moderate according to the GRADE system.
CONCLUSION: VR-based interventions probably reduce neuropathic pain intensity in individuals with SCI. Further well-designed, adequately powered RCTs are warranted to confirm the magnitude and durability of this effect.
| Discipline Area | Score |
|---|---|
| Physician | 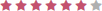 |
| Rehab Clinician (OT/PT) | |
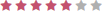
Physician rater
Virtual reality may serve as a low-risk supplement to drug therapy in rehabilitation programs for patients with SCI and neuropathic pain. Home-use headsets could increase treatment sessions. Next steps should include conducting powered multicenter RCTs, establishing a standardized dose, ensuring follow-up exceeds 6 months, and implementing phenotype-based patient selection.
Physician rater
VR is a reasonable adjunct rather than a replacement for pharmacotherapy. The meta-analysis did not differentiate pain levels or analyze the use of concomitant analgesics. There were no reports based on MCID or responder analysis, and adverse events were not aggregated. Most outcomes were immediate or short-term. Blinding procedures were weak, some trials experienced high attrition, and comparator groups varied from sham to TENS.






 , McMaster University